TB-500 and thymosin β4
A short fragment carries a much longer protein’s reputation. Before arguing over the findings, I want both molecular lengths on the table.
The seven-residue fragment
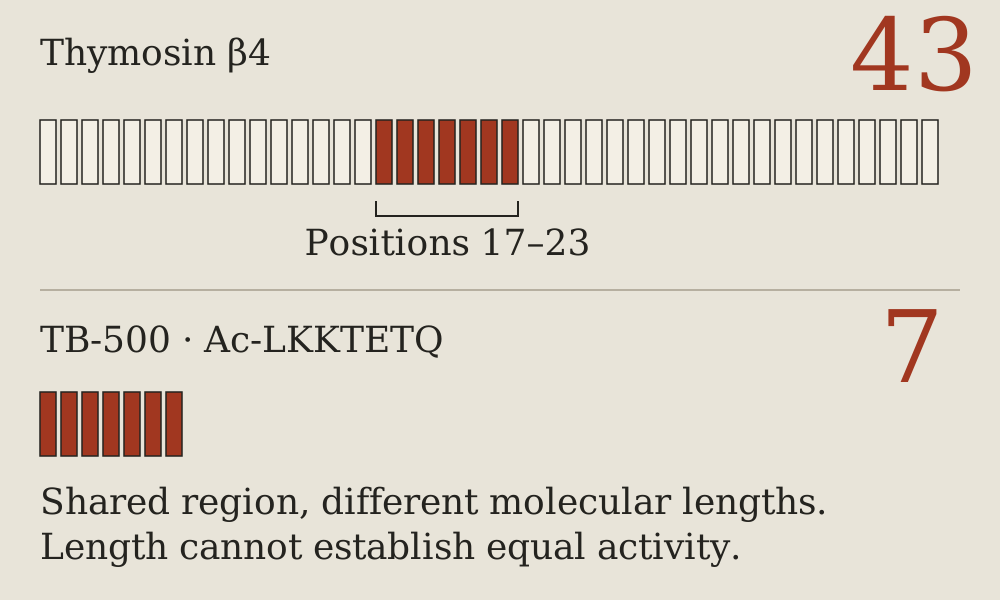
TB-500 denotes the synthetic acetylated fragment Ac-LKKTETQ, corresponding to residues 17–23 of thymosin β4. Full-length thymosin β4 contains 43 amino acids; the fragment contains seven. Its shared sequence includes the parent's actin-binding region.
The 2012 review of thymosin β4 describes the full protein's biology and clinical rationale. The 2026 musculoskeletal review places TB-500 among unapproved peptide therapies with scarce rigorous human safety data.
I can imagine useful activity surviving in that shared region. Its presence alone cannot decide how much of the parent's behaviour survives. The controlled human record for the isolated TB-500 fragment remains empty.
Neurological outcomes in rats
The 2014 stroke dose-response experiment used full-length thymosin β4 in male Wistar rats after embolic middle cerebral artery occlusion. Neurological function improved at the studied amounts of 2 and 12 mg/kg, significantly from day 14 through day 56 (p<0.05). The highest tested amount, 18 mg/kg, produced no significant benefit.
The uneven response is the interesting wrinkle for me. Increasing the study amount did not produce a steadily larger effect. These were animal-study amounts, administered intraperitoneally after an experimental stroke; they supply no human regimen.
The outcome was neurological function after a brain injury. Attributing it to the seven-residue fragment would require another experiment, and describing it as human peripheral nerve regeneration would require a different clinical result altogether.
Full-length thymosin β4 in volunteers
The randomised placebo-controlled Phase 1 study gave synthetic full-length thymosin β4 intravenously to 40 healthy volunteers. It was well tolerated, with infrequent mild-to-moderate adverse events, no dose-limiting toxicities and no serious adverse events. Pharmacokinetics were dose-proportional, and half-life increased at higher doses.
A controlled safety study earns my respect. The ingredient and the purpose still matter: these volunteers received the parent protein, and the trial assessed safety and pharmacokinetics. It leaves the fragment's safety and treatment efficacy unresolved.
Actin and cellular movement
Actin is part of the machinery cells use to change shape and move. The 2004 structural study examined a gelsolin-domain-1–thymosin β4 hybrid bound to actin. It established how thymosin β4 forms a one-to-one complex with monomeric actin and caps both ends, holding it back from polymerisation.
The multi-model review connects the full-length parent protein with cell migration, reduced myofibroblast numbers and scar formation, and angiogenesis in injury models. These mechanisms provide a rationale for clinical trials of the full-length protein. Most of the protein has vanished from the explanation. That omission bothers me.
TB-500 safety
Community accounts describe easier movement and recovery from tendon, ligament or muscle injuries. Local soreness, swelling, tiredness, headache, lightheadedness and occasional nausea appear alongside the favourable accounts. They are anecdotal reports, not clinical evidence for the TB-500 fragment.
The parent protein's pro-migratory and pro-angiogenic properties raise a theoretical tumour-growth concern. That risk has not been measured for TB-500 in people. Bleeding, surgery, pregnancy, breastfeeding and use in the young also remain precautionary questions with no fragment-specific human safety data. Calling the empty human record reassuring would be a strange reading of it.
The 2026 safety review describes potential for serious harm and limited oversight among unapproved peptides. Research-grade identity and purity add further uncertainty. TB-500 has no approved therapeutic indication and is supplied for laboratory research, with a veterinary history. WADA prohibits it under peptide and growth-factor categories; anti-doping detection methods exist.